


Hysterectomy coding is not as straightforward as it looks. In fact, it can be one of the more complicated surgical categories to code. The correct CPT code depends on the route, whether the cervix was removed, whether the tubes or ovaries were removed, whether the uterus weighed 250 grams or less or more than 250 grams, and whether extra work such as enterocele repair, colpo-urethrocystopexy, lymph node sampling, radical dissection, or tumor debulking was done.
CMS coding policy is clear that the reported code has to match the procedure performed as specifically as possible, and ACOG’s coding guidance separates laparoscopic hysterectomy into distinct code families for that reason.
| A hysterectomy is the removal of the uterus. A total hysterectomy removes the uterus and cervix. A supracervical hysterectomy removes the upper uterus but leaves the cervix in place. A radical hysterectomy removes the uterus, cervix, and surrounding tissue and is generally tied to cancer-related surgery. |
Hysterectomy may be performed through an abdominal, vaginal, laparoscopic, or robotic-assisted approach, and for benign disease ACOG notes that vaginal and laparoscopic routes are minimally invasive options, with the vaginal route preferred when feasible.
What drives hysterectomy CPT code selection
For coding purposes, the operative report has to answer a short list of questions.
- First, what was the surgical approach: open abdominal, vaginal, laparoscopic, or laparoscopic-assisted vaginal?
- Second, was the procedure total, supracervical, or radical?
- Third, were the tubes and/or ovaries removed?
- Fourth, for many vaginal and laparoscopic code families, was the uterus 250 grams or less or greater than 250 grams?
- Fifth, was there additional work such as enterocele repair, colpo-urethrocystopexy, vaginectomy, lymphadenectomy, or tumor debulking?
Those are not some minor details, they move the claim from one code family to another.
Abdominal hysterectomy CPT codes

- The most commonly cited open abdominal code is 58150.
This covers a total abdominal hysterectomy involving the corpus and cervix, with or without removal of the tubes and with or without removal of the ovaries.
- If the case is open abdominal but the cervix is left in place, the code shifts to 58180
This one is the supracervical or subtotal abdominal hysterectomy code.
- Next is 58152.
If a total abdominal hysterectomy is done with colpo-urethrocystopexy, the code moves to 58152 rather than a plain 58150.
The abdominal family also includes more extensive oncology-related work.
- Public code references show 58200 for total abdominal hysterectomy
Includes partial vaginectomy and lymph node sampling
- 58210 for radical abdominal hysterectomy
Bilateral total pelvic lymphadenectomy and para-aortic lymph node sampling, with or without removal of tubes or ovaries.
- At the far end of the spectrum is 58240, which CMS NCCI treats as a pelvic exenteration code.
That is not a routine benign hysterectomy code. CMS specifically states that with pelvic exenteration procedures such as 58240, physicians should not separately report removal of pelvic structures like the bladder, rectum, uterus, cervix, tubes, ovaries, or lymph nodes because those components are already part of the exenteration work.
Abdominal coding starts simple with total versus supracervical hysterectomy, then gets more specific when the case includes bladder-neck support work, vaginectomy, radical dissection, nodal work, or exenteration-level surgery. That is why the op note cannot stop at “TAH.” It has to show whether the cervix stayed or went and whether there was added oncologic or reconstructive work.
Vaginal hysterectomy CPT codes
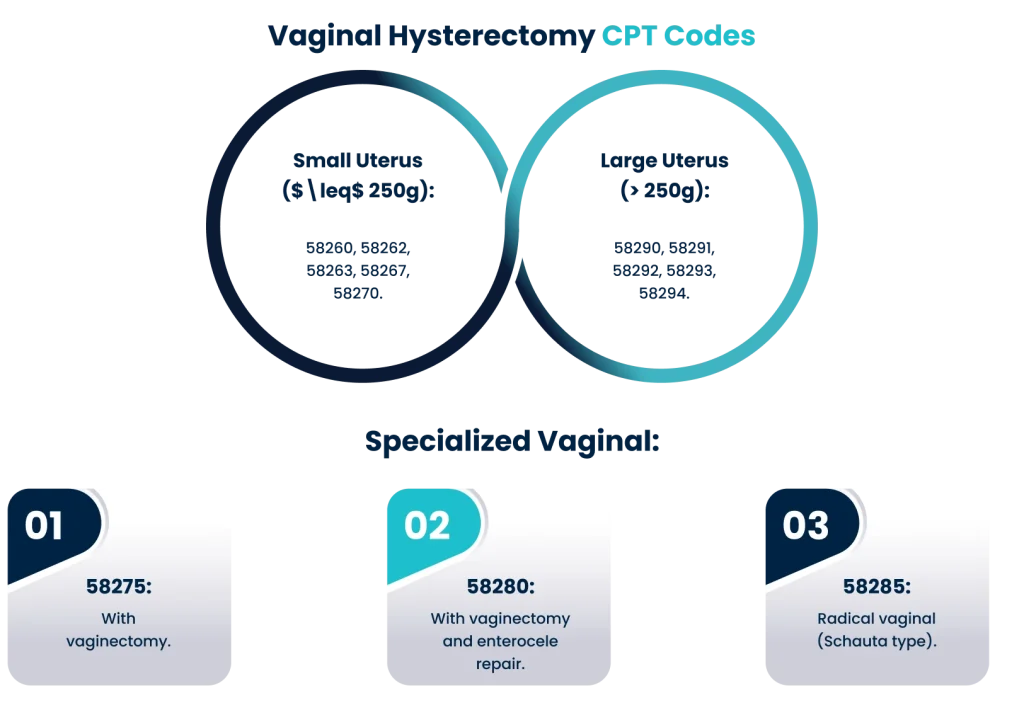
The vaginal family is more layered than many coders expect.
- For a uterus 250 grams or less, the base vaginal hysterectomy code is 58260.
- If the same size uterus is removed vaginally with removal of tubes and/or ovaries, the code becomes 58262.
- If there is vaginal hysterectomy for a uterus 250 grams or less with removal of tubes and/or ovaries and repair of enterocele, the code is 58263.
- If the same size uterus is removed vaginally with colpo-urethrocystopexy, the code is 58267.
- If the same size uterus is removed vaginally with repair of the enterocele, the code is 58270.
- There is a separate vaginal family for a uterus greater than 250 grams. In that group, 58290 is the base vaginal hysterectomy code.
- 58291 adds removal of tubes and/or ovaries.
- 58292 covers removal of tubes and/or ovaries with repair of enterocele.
- 58293 covers the larger-uterus vaginal hysterectomy code with colpo-urethrocystopexy.
- 58294 covers the larger-uterus vaginal hysterectomy code with repair of the enterocele. The 250-gram threshold is not a footnote here. It is one of the main things that determines whether you are in the 58260-family or the 58290-family.
- There are also less common but still important vaginal codes outside the basic weight-based families.
- 58275 is used for vaginal hysterectomy with total or partial vaginectomy. 58280 adds repair of enterocele to that vaginectomy-based vaginal hysterectomy. 58285 is the radical vaginal hysterectomy code, listed publicly as the Schauta type operation.
These are not codes you reach by assumption. They require clear operative language showing vaginectomy or radical vaginal work, not just a standard vaginal hysterectomy.
One of the easiest places to lose revenue or trigger edits in this family is bundled adnexal work. CMS NCCI gives a direct example: if the surgeon performs a vaginal hysterectomy on a uterus under 250 grams with bilateral salpingo-oophorectomy, the correct code is 58262, not 58260 plus 58720. In other words, if a combination code already captures the adnexal removal, do not fragment the case into separate component codes.
Laparoscopic hysterectomy CPT codes

Laparoscopic coding is where a lot of coding guides go wrong, because they mix together code families that are not interchangeable. ACOG’s coding guidance separates laparoscopic hysterectomy into three main families: laparoscopic supracervical hysterectomy, laparoscopic-assisted vaginal hysterectomy, and total laparoscopic hysterectomy. Each family has its own code logic.
The laparoscopic supracervical hysterectomy family uses 58541 to 58544.
The total laparoscopic hysterectomy family uses 58570 to 58573. This is one of the most commonly miscoded groups. ACOG’s coding chart shows the correct breakdown: 58570 is total laparoscopic hysterectomy for a uterus 250 grams or less without removal of tubes or ovaries, 58571 is the same weight range with removal of tubes and/or ovaries, 58572 is for a uterus greater than 250 grams without adnexal removal, and 58573 is for a uterus greater than 250 grams with removal of tubes and/or ovaries. That sequence is important, because a lot of weak content online flips 58571 and 58572.
CPT code for robotic hysterectomy

Robotic hysterectomy does not have its own standalone CPT hysterectomy family. The base CPT code still comes from the underlying laparoscopic procedure that was performed. In other words, the coder selects the correct laparoscopic hysterectomy code first, then checks payer policy to see whether HCPCS S2900 should be reported as a secondary code for robotic assistance.
The Society of Gynecologic Oncology states that S2900 may be reported when required by the payer, and that it is not necessary to append a modifier. The same guidance also states that CMS has chosen not to create a modifier or specific CPT code for robotic surgery that would drive extra payment.
CMS materials on HCPCS policy likewise note that Medicare generally treats the robotic system cost as part of the procedure payment rather than something separately payable.
That also means you should not switch to an open code just because the surgeon used a robot. SGO’s coding guidance says it is not appropriate to report an open procedure code for a procedure performed laparoscopically, and if there is no corresponding laparoscopic code, an unlisted code is the route, not an open code by default. SGO also notes that if a laparoscopic case is converted to open, the usual recommendation is to bill the open procedure code only, with modifier 22 considered only when the documentation supports substantial extra work.
Documentation points that make or break the claim
If you want clean hysterectomy coding, the operative report needs to spell out a few items every time:
- The route
- Whether the cervix was removed?
- The uterus weight when the code family uses the 250-gram threshold
- Whether tubes and/or ovaries were removed?
- Whether there was enterocele repair or colpo-urethrocystopexy?
- Whether vaginectomy was done?
- Whether the case involved radical dissection or nodal work?
- Whether the case involved malignancy debulking?
Those are the items that move the case across code families.
From a compliance angle, CMS coding policy gives two basic rules that apply all the way through hysterectomy coding.
- First, report the HCPCS/CPT code that describes the procedure performed to the greatest specificity possible.
- Second, do not report multiple codes when a single existing code already describes the service. That is the logic behind combination hysterectomy codes and the reason unbundling errors happen so often in this space.
Common hysterectomy coding mistakes to avoid
- One common mistake is mixing up LAVH, TLH, and LSH as if they were interchangeable laparoscopic labels. They are not. ACOG separates them into different code sets because the surgical work is defined differently. Another frequent error is ignoring the 250-gram uterus threshold in the vaginal and laparoscopic families. That detail changes the code.
- Another mistake is treating robotic assistance as if it creates a separate hysterectomy CPT family. It does not. The case is still coded from the underlying laparoscopic family, with S2900 only if the payer wants it. A related mistake is reporting an open code for a robotic or laparoscopic case simply because the surgeon used different equipment. SGO specifically warns against that.
- Unbundling is another big one. If a combination hysterectomy code already includes removal of tubes and/or ovaries, do not add a separate salpingo-oophorectomy code on top of it. CMS NCCI gives a direct example with 58262 versus 58260 plus 58720. The same principle applies more broadly across hysterectomy coding. If one code already captures the full work, do not split it into pieces.
Don’t let 250g thresholds or route errors trigger audits. Partner with BilNow OB/Gyn billing & coding specialists for 100% accuracy.

Final word
The safest way to code hysterectomy is to stop thinking in labels like “simple,” “robotic,” or “lap hyst” and start coding from the actual operative details. Route, cervix status, adnexal removal, uterus weight, repair work, radical dissection, and malignancy-related work all drive code selection. If the note clearly states those facts, the code choice usually becomes straightforward. If the note is vague, the claim gets risky fast.
For final claim submission, use the current CPT/HCPCS code set, payer policy, and the operative report together. Public CMS, NLM, ACOG, and SGO materials are helpful for structure and coding logic, but the submitted claim still has to match the exact documented procedure and the payer’s billing rules on the date of service.
FAQs About Hysterectomy CPT Codes
What is the CPT code for a hysterectomy?
There is no single CPT code for all hysterectomies. The correct code depends on the surgical route, whether the cervix was removed, whether the tubes and/or ovaries were removed, whether the uterus weighed 250 grams or less or more than 250 grams, and whether additional work such as repair, lymph node sampling, or radical dissection was performed.
What is the CPT code for a total laparoscopic hysterectomy?
For total laparoscopic hysterectomy, the code set is 58570 to 58573. 58570 is used when the uterus is 250 grams or less and the tubes or ovaries are not removed. 58571 is used when the uterus is 250 grams or less and the tubes and/or ovaries are removed. 58572 is used when the uterus is greater than 250 grams without adnexal removal, and 58573 is used when the uterus is greater than 250 grams with removal of the tubes and/or ovaries.
What is the CPT code for a vaginal hysterectomy?
For a vaginal hysterectomy with a uterus weighing 250 grams or less, the base code is 58260. If the same procedure includes removal of the tubes and/or ovaries, coders usually look to 58262 instead of reporting separate component codes. For a uterus greater than 250 grams, the vaginal hysterectomy family shifts to codes such as 58290 and related combinations depending on the work performed.
What is the CPT code for an abdominal hysterectomy?
A standard total abdominal hysterectomy is commonly reported with 58150. If the cervix is left in place, the code changes to 58180, which is the supracervical or subtotal abdominal hysterectomy code. More extensive open procedures, such as radical surgery or cases with additional pelvic work, may fall under different codes in the abdominal hysterectomy family.
Is robotic hysterectomy coded differently?
Robotic hysterectomy does not have its own standalone CPT hysterectomy family. The case is coded using the underlying laparoscopic hysterectomy code, and some payers may require HCPCS code S2900 as a secondary code to show robotic assistance. Recognition of S2900 varies by payer, and Medicare generally does not reimburse S-codes.
What is the difference between a total hysterectomy and a supracervical hysterectomy?
A total hysterectomy removes the uterus and cervix. A supracervical hysterectomy removes the upper part of the uterus but leaves the cervix in place. That distinction affects both procedure documentation and CPT code selection.
Does uterus weight affect hysterectomy CPT coding?
Yes. In several vaginal and laparoscopic hysterectomy code families, the code changes depending on whether the uterus weighed 250 grams or less or more than 250 grams. If the operative report does not clearly document uterus weight where required, final code selection can become inaccurate or incomplete.
Can tubes and ovaries be coded separately with a hysterectomy?
Not always. If the hysterectomy code already includes removal of the tubes and/or ovaries, those components should not be billed separately. CMS NCCI specifically warns against fragmenting procedures into component parts when a single code already describes the full service.
If a laparoscopic hysterectomy is converted to open, what should be billed?
When a laparoscopic hysterectomy is converted to an open procedure, coding guidance from SGO states that the open procedure code is generally billed, not both the laparoscopic and open procedure codes together. Modifier 22 may be considered only when the documentation supports substantially greater work than usual.
What documentation is most important for hysterectomy CPT coding?
The operative report should clearly show the surgical approach, whether the cervix was removed, whether the tubes and/or ovaries were removed, uterus weight when relevant, and any additional work such as enterocele repair, colpo-urethrocystopexy, lymph node sampling, radical dissection, or tumor debulking. Without those details, accurate code selection becomes harder and denials become more likely.


