


Congress created Medicaid on July 30, 1965, and the program changed how the United States financed healthcare for low-income patients. Before this social security milestone, financially vulnerable families, eligible disability beneficiaries and the elderly persons lacked a unified medical safety net. With roughly 75.3 million enrollees nationally, Medicaid and the Children’s Health Insurance Program (CHIP) include 40% of the nation’s children while protecting the well-being of 1 in 5 Americans. (CMS / Kaiser Family Foundation)
There is an unbalanced high rate of rejections and denials of Medicaid claims across the industry. The structure of Medicaid that makes it a compulsion for practices to work in a decentralized, state-by-state administrative patchwork is the core reason for increased denials. These varying local rules when combined with rapid enrollment fluctuations also known as “eligibility churn” have taken a financial toll on medical practices. It is no longer helpful to consider Medicaid as a secondary administrative follow-up thought. Revenue velocity now depends on a stronger front-end billing strategy because Medicaid claims carry stricter eligibility, coding, documentation, and payer-rule demands.
What are Medicaid and Medicaid MCOs?
Medicaid is a joint federal and state health insurance program that provides medical coverage to eligible low-income individuals, families with children, pregnant women, the elderly, and people with disabilities. Although the baseline criteria is determined by the federal government, each state has the right to manage the program on its own. This results in the formation of 50 distinct coverage rules sets, fee schedules and filing limits timely. As providers cannot depend solely on universal billing template, so claims must correspond directly to hyper-local state guidelines.
The Medicaid programs are widely contracted out to private insurers known as Medicaid Managed Care Organizations (MCOs) in order to bring stability in state budgets and improve administration control. For public healthcare, these capitation MCOs have now become the most predominant delivery systems. The date tracked by the Kaiser Family Foundation (KFF) has revealed that over 66 million individuals, which make up almost 78% of all Medicaid beneficiaries nationwide, are given their coverage through private MCO plans instead of traditional state-run fee-for-service infrastructure.
Medicaid vs. Medicare: The Core Architectural Differences
The application of standardized Medicare logic to Medicaid accounts is one of the most common billing errors. Although both programs are under the control of the Centers for Medicare & Medicaid Services (CMS), both are completely different in their structural funding, compliance standards and payment rules.
| Operational Vector | Medicare | Medicaid |
| Oversight & Rule Authority | Purely Federal Rules are uniform across all 50 states | Joint Federal-State Administered by individual states under broad federal guidelines |
| Target Population | Individuals aged 65+, or those under 65 with specific qualifying disabilities (e.g. ESRD) | Low-income individuals, families, children, pregnant individuals and disabled adults |
| Enrollment Portal | Centralized federally via the PECOS system | Individual state-specific Medicaid provider enrollment portals |
| Claim Rules Consistency | Identical code edits and fee schedules nationwide | Highly variable rules, modifiers and coverage boundaries shift at state lines |
| The Payer of Last Resort Rule | Can act as primary insurance or secondary coverage depending on employer plans | Strictly the payer of last resort. All other primary options must be exhausted first. |
Who Qualifies to Bill for Medicaid?
For legal billing of Medicaid, holding an active medical license is not enough. The provider has to complete a detailed formal onboarding process.
To start the credentialing process a provider must have a NPI , a taxonomy code, an official IRS letter (CP575 or 147C) and a copy of degree. Additionally, an active Professional Liability Insurance (PLI) and an EFT-linked voided business check are also required. Moreover, getting through the compulsory federal background screens against the HHS OIG sanction database is must for all applicants to get an authorized status.
When all the credentials are correctly provided, Medicaid approves speciality providers and facilities to treat the patients. These providers are grouped into the following categories:
- Individual Practitioners: Physicians (MD/DO), Nurse Practitioners (NPs), Physician Assistants (PAs), Podiatrists, Dentists and Optometrists
- Behavioral Health and Therapy Providers: Licensed Clinical Social Workers (LCSWs), Board Certified Behavior Analysts (BCBAs), Physical Therapists (PTs), Occupational Therapists (OTs) and Speech-Language Pathologists (SLPs)
- Institutional Facilities: Acute care hospitals, Rural Health Clinics (RHCs), Federally Qualified Health Centers (FQHCs) and skilled nursing facilities
- Ancillary Suppliers: Durable Medical Equipment (DME) providers, laboratory networks and non-emergency medical transportation (NEMT) services
The Medicaid Billing Process: Step-by-Step
The life cycle of a Medicaid claim requires tight front-end operational controls. Because patient eligibility status shifts frequently due to income adjustments, any slip in validation breaks the entire workflow. To safeguard your cash flow, practices must implement precise quality checks across each distinct phase of the submission pipeline.
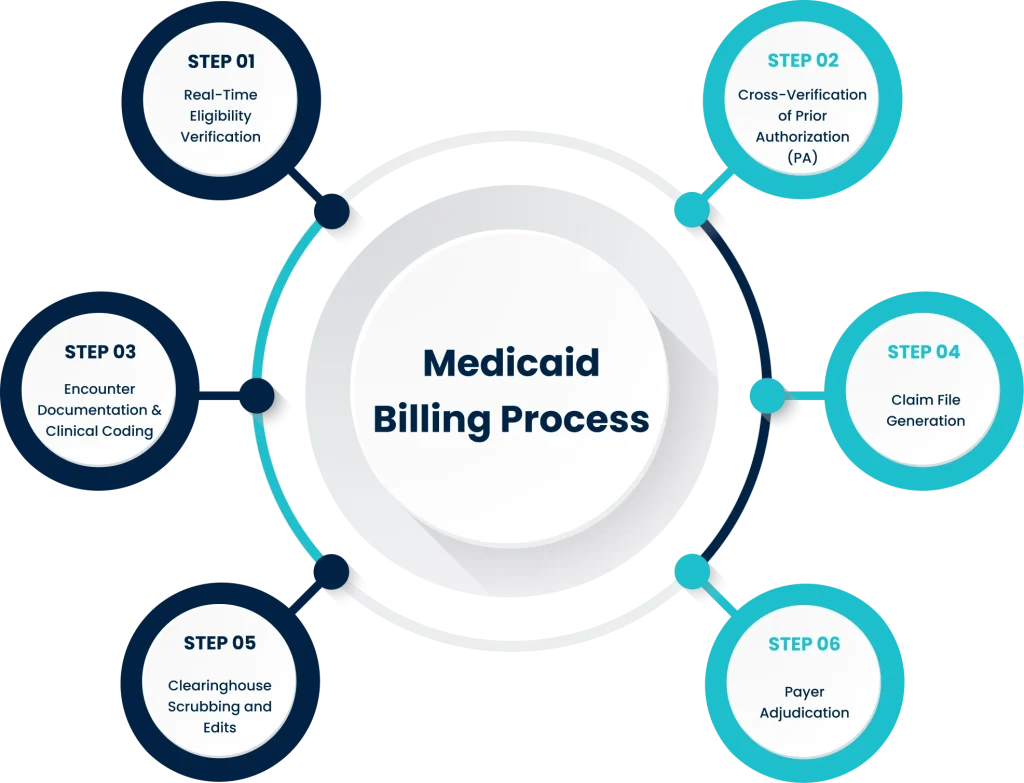
Step 1: Real-Time Eligibility Verification
Front-Desk staff must check patient eligibility two days prior to the appointment to confirm whether the patient will be In-Network. The team should also validate whether the patient is a standard Fee for Service or a Private MCO Beneficiary, as claim routing differs in both cases. It must also be confirmed that the patient does not have any active Primary Commercial Insurance or Medicare, as Medicaid is the payer of last resort. Failing to do this will result in automatic coordination of benefits (COB) denials.
Step 2 — Cross-Verification of Prior Authorization (PA)
When Medicaid requires Prior Authorization (PA) for a specific service, billing teams need to link an approved tracking token to their system before the service is provided. If there are limits to how many appointments the Prior Authorization applies to, staff will need to keep track of how many service units are remaining to avoid exceeding the treatment limit. If services are provided without taking unit limits into account, it will result in a hard denial. These denials are permanent and cannot be overturned, even if medical records are reviewed after the fact.
Step 3 — Encounter Documentation & Clinical Coding
Medical professionals are required to provide a descriptive account of the encounter so that coders are able to assign the appropriate CPT, HCPCS, and specific ICD-10-CM codes. Blocks for validation must ensure that encounter documentation and coded traffic are in agreement with unit parameters. Teams are also required to apply local unit and state modifier requirements, review documentation, and align traffic with edits to the National Correct Coding Initiative before submission for denial prevention.
Step 4 — Claim File Generation
EHR systems, including but not limited to Tebra, TherapyNotes, and Simple Practice, create claim files that include an electronic 837P or 837I embedded with your unique state Medicaid ID. Assume an example where there exists a slight typographical error within Loop 2010AA or Loop 2420A. Billing staff must also ensure that the provider’s taxonomy codes are verified against the state registries, as an invalid code would also result in a rejection from the Clearinghouse.
Step 5 — Clearinghouse Scrubbing and Edits
Medicaid claims are then sent to a Clearinghouse via EDI. The Clearinghouse will conduct a pre-adjudication by applying structural formatting and baseline compliance checks. Medicaid scrubbing, in particular, is highly specialized due to its locality and tends to be a greater risk when using off-the-shelf commercial scrubbing templates. Billing departments tend to employ their own medical scrubbing techniques tailored to the specific Medicaid MCO plan contract requirements and create their own timely filing and technical rule boundaries.
Step 6 — Payer Adjudication
During this step, either a state agency or a private MCO will review the claim file against their own definitions of medical necessity. The payer will also determine if the submission meets their benefit limits and falls within their payment schedule. Meanwhile, the billing staff must begin tracking the 835 Electronic Remittance Advice (ERA) files on a daily basis as they need to avoid leaving unreturned files in a passive “pending payment” state. Through this proactive approach, the staff address claim adjustment codes upholding compliance with state dispute windows. This allows them ample time to file appeals prior to the claim adjustment window closing.
Common Medicaid Billing Mistakes
State-Specific rules, along with increased scrutiny by MCO plans, make Medicaid billing a challenge for healthcare practices. Some of the most prevalent errors you should be wary of while doing Medicaid Billing are as follows:
- Front-desk staff sometimes overlook the importance of checking eligibility because they have already verified it in the recent past. As Medicaid status is strictly governed by ever-evolving state rules and the latest income of the beneficiary, neglecting eligibility can lead to services being rendered to an inactive patient.
- The coding team is at times too focused on applying the right CPT, HCPCS & ICD Codes. They end up ignoring state-specific modifiers, which are deemed mandatory under the concerned state’s fee schedule, which can lead to a claim denial.
- For certain services, Medicaid and Medicaid MCOs compel the provider to obtain prior authorization. If the service codes, dates or unit volumes are not in accordance with the pre-approved prior authorization (PA) token, a hard denial will be triggered.
- The Accounts Receivable (A/R) Team sometimes mistakes Medicaid MCOs for commercial insurance. Unknowingly, they breach the timely filing limit for claims set forth by Medicaid, leading to a delay in submission. It leads to AR Aging.
- The NPI of the rendering provider must exactly match the Taxonomy Code under which the provider was enrolled with the State Medicaid Program. Consistent discrepancies in this process will lead to a medical audit by Medicaid.
Tired of Medicaid Denials?
BILNOW’s dedicated billing specialists eliminate state-specific errors to slash your denial rates and accelerate your cash flow.

Specialty-Specific Medicaid Billing Rules
Standard commercial coding logic fails when applied to specialized Medicaid benefit categories. To prevent automated front-end rejections, billing workflows must accommodate hyper-local and specialty-specific constraints across three high-risk sectors which are:
Behavioral Health (ABA)
Medicaid heavily scrutinizes multi-tiered rendering credentials. You must append explicit modifiers such as HN for Bachelor ’s-level assistants or HM for Registered Behavior Technicians (RBTs) to standard 15-minute codes like 97153. Mismapping the clinical supervisor versus the direct technician triggers instant double-billing rejections.
Pediatrics & EPSDT
Under the federal Early and Periodic Screening, Diagnostic and Treatment (EPSDT) mandate, beneficiaries under age 21 are legally exempt from standard adult care ceilings. If documentation proves medical necessity, EPSDT overrides state-level “soft limits” on therapy or prescriptions, allowing you to bypass automated system blocks.
Rehabilitative Therapies (PT/OT/SLP)
Claims will be rejected outright without mandatory discipline designators like GP (Physical Therapy), GO (Occupational Therapy) or GN (Speech Therapy). Furthermore, billing same-day multi-disciplinary sessions requires distinct documentation and modifiers to bypass localized daily combination caps.
Frequently Asked Questions
How do I get a Medicaid billing number?
To get a Medicaid billing number, one has to enroll through their state’s specific Medicaid provider portal. An active National Provider Identifier (NPI), a Federal Tax ID Number (TIN/EIN), current state licensure and matching specialty taxonomy codes are necessary for registration.
How long does it take to get paid from Medicaid?
The payment timelines depend on plan structure. Usually 14 to 30 days are required to clean electronic claims sent to private MCOs. Traditional state-run Fee-for-Service (FFS) programs take 30 to 45+ days as they operate on fixed state budget cycles.
Can I bill Medicare and Medicaid at the same time?
Yes, Medicare and Medicaid can be billed at same time for “dual-eligible” patients. Being the primary insurance provider, the claim must be first determined by Medicare. After processing, the remaining balance is transferred to Medicaid which is the secondary payer of last resort.
Is Medicaid billing the same in every state?
No. Although all 50 states share the same standard CPT, HCPCS, and ICD-10 medical codes, each state has its own operational rules. The factors varying across the states include reimbursement rates, prior authorization triggers, hyper-local modifier mandates and timely filing deadlines.
Do providers need prior authorization for all Medicaid services?
No. Prior authorization is required for high-cost diagnostics, specialized therapies, durable medical equipment (DME) and non-routine surgical operations. Routine office visits, preventative screenings and emergency medical interventions generally do not require prior authorization.
What is the difference between Medicaid and Medicaid Managed Care billing?
In Medicaid traditional Fee-for-Service (FFS), claims have to be submitted to state agencies while keeping in view the standard state fee schedules. However in Medicaid Managed Care, private insurance networks (MCOs) like UnitedHealthcare or Molina are involved. One has to contract with and bill those individual private networks using their specific authorization rules.
How do providers appeal denied Medicaid claims?
The first step is to locate the exact point of failure by analyzing the claim adjustment reason codes (CARCs). It is followed by compilation of a formal appeal packet containing the state-specific form, a denied claim copy and documents for proving the medical necessity. This appeal must be submitted in a 30 to 60 day window through the payer portal.


